
Keratoconus · Concord Eyecare, North Strathfield, Sydney
Keratoconus: what it means and what happens next
Just been told you have keratoconus, or that it’s changing? Here’s what it is, whether it is likely to get worse, and every option for treating it: the lenses we fit here, and the surgical side we arrange with a corneal surgeon.
On the booking page, choose Scleral Lens Consultation. For other keratoconus visits, call us on (02) 8765 9600.
- ★ 4.9 from 200+ Google reviews
- Additional qualifications All of our optometrists hold additional qualifications to deliver a high standard of care
- All health funds HICAPS on the spot
What is keratoconus?
The cornea thins and bulges into a cone
Your cornea should be a smooth, evenly curved dome. In keratoconus it thins, and the pressure inside your eye pushes it outward into a cone. Because the surface is no longer regular, light entering the eye scatters instead of landing in one place. That is why the blur has a smeary, ghosted quality that new glasses never quite clear.
A normal cornea
A cornea with keratoconus
Simplified illustrations. They are not scans, not to scale, and not a real patient. The dashed line on the right shows where a normal cornea would sit. How much your own vision is affected depends on how far the cone has developed, and it is different for everyone.
Most people notice it as vision that keeps changing. You get new glasses, they help for a while, and then they don’t. Straight edges look bent or doubled. Lights at night grow tails and haloes. One eye is often worse than the other.
Glasses bend light uniformly. A cone isn’t uniform.
That is the whole reason glasses stop keeping up — and the reason every treatment that follows works the way it does. It is not a failure of your glasses, or of whoever prescribed them. It is the geometry.
Keratoconus is also more common than it was once thought to be. The Raine Study in Perth, an Australian study, scanned 1,259 twenty-year-olds and found corneal changes consistent with keratoconus in about 1 in 84. That figure comes from imaging everyone rather than waiting for symptoms, so it picks up very early changes that would never otherwise have been diagnosed. In short: early keratoconus is common, and severe keratoconus is not.
We manage pellucid marginal degeneration along the same lines. It is a related thinning that sits lower on the cornea, and the approach is the same: map it, watch it, correct it with the right lens.
Will I go blind from keratoconus?
Watched and treated, most people keep their sight
Keratoconus can cause serious vision loss if it goes unchecked. As it advances the cornea keeps steepening and can scar, until no lens gives usable vision and a corneal transplant becomes the option. That is exactly why the monitoring and the treatments on this page exist.
The risk at the far end is real.
Advanced keratoconus can reach the point where lenses no longer work and grafting is the remaining option. In one Belgian series, 75 eyes with severe keratoconus were all transplant candidates by the time they were seen. The same series showed how much can still be done at that stage (further down this page).
But it usually progresses slowly, and often settles.
Keratoconus is most active through the teens and twenties and tends to quieten after that. In the Australian randomised trial in Melbourne, untreated eyes steepened by roughly 1.75 dioptres over three years: real change, but gradual and measurable long before you feel it. Most people who are picked up and monitored keep good functional vision for life.
And there is one sudden event worth knowing about.
Very occasionally the inner layer of a thin cornea splits and fluid floods in (hydrops). Vision goes cloudy suddenly, often with pain and light sensitivity. It usually settles over weeks to months, but needs to be seen straight away.
Which is the whole argument for catching it early.
Nearly everything that leads to the bad outcome is slow, silent and measurable. Cross-linking is designed to stop the steepening, and works best while there is still cornea worth protecting. So the useful question is whether yours is changing, and a scan answers that.
Call us the same day if: your vision goes cloudy or drops suddenly, your eye becomes painful and red, or you develop new sensitivity to light. These are not things to sit on over a weekend.
Keratoconus treatment options
Lenses help you see; cross-linking holds the cornea steady
Most people need a plan for both, and this is where most of the confusion comes from. Being told you need cross-linking and that you need scleral lenses is not two opinions competing. It is two different jobs. Lenses do not stop progression, and cross-linking does not sharpen vision.
Job one
Seeing well
Done with lenses: glasses while they still keep up, then rigid or scleral contact lenses as the cone steepens. This is the half that changes your day.
Job two
Holding the cornea steady
Done with corneal cross-linking, a hospital procedure that stiffens the cornea’s internal bonds. This is the half aimed at stopping progression.
They work together rather than competing. Whether your cornea is changing decides which of them you need and in what order. That is what the monitoring further down this page is for.
Fitted here at Concord Eyecare
the seeing-well half
Glasses
Fine for early keratoconus, while the shape is still regular enough for a spectacle lens to correct. If glasses are working, there is no reason to change.
Soft toric contact lenses
An option in mild cases with regular-enough astigmatism. Limited once the cone steepens, because a soft lens drapes over an irregular surface rather than correcting it.
Corneal rigid gas permeable lenses
A small rigid lens that sits on the cornea and forms its own smooth front surface. Excellent optics. Comfort is the usual limitation, and the usual reason people move on.
Scleral lenses
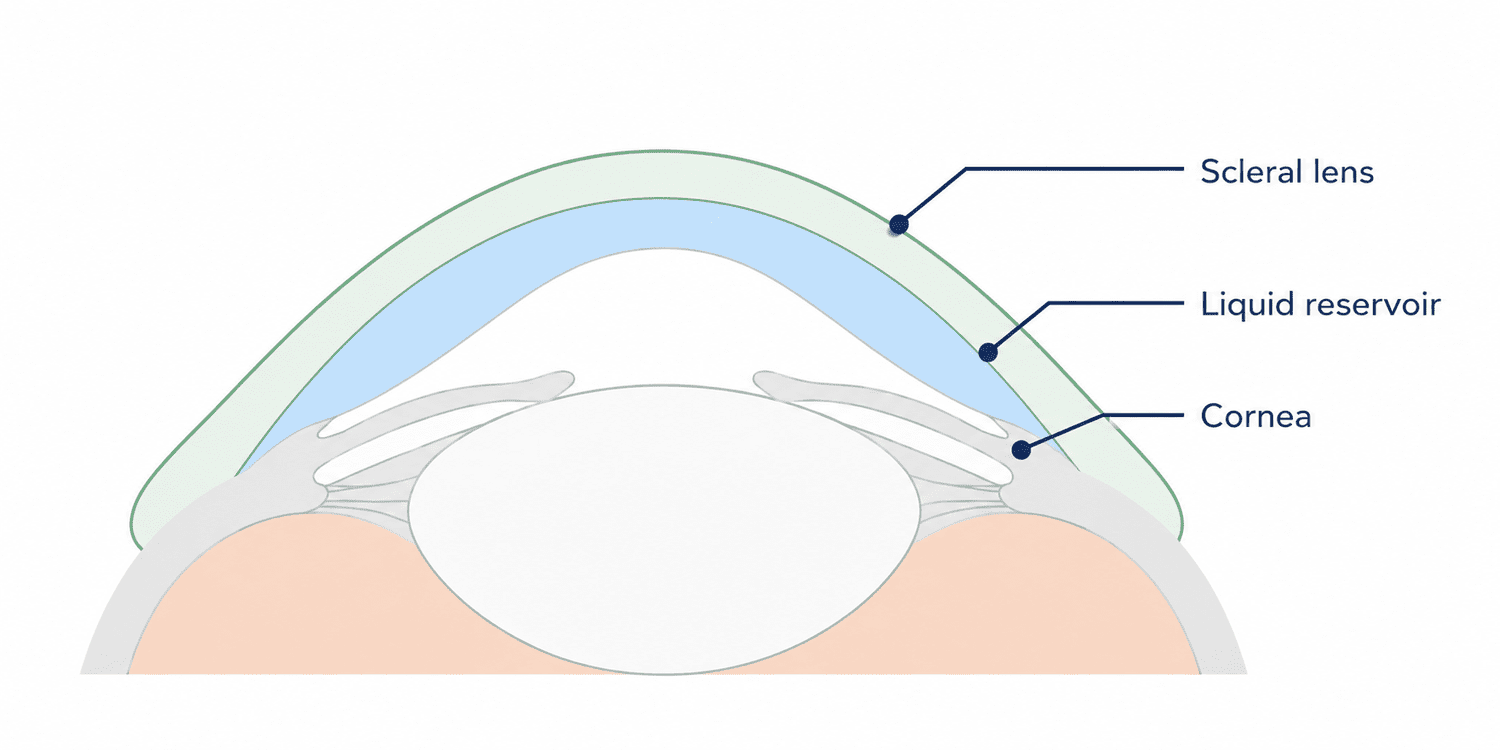
A larger rigid lens that vaults right over the cone and rests on the white of the eye, with fluid held underneath. Comfortable and stable when smaller lenses have not worked out.
Referred to a corneal surgeon
we don’t perform these, and we’ll organise the referral
Referred
Corneal cross-linking (CXL)
The treatment aimed at stopping progression. Riboflavin drops plus controlled ultraviolet light stiffen the bonds inside the cornea. This is the one that matters most if your cornea is changing.
Referred
Intracorneal ring segments
Small implants placed within the cornea to flatten the cone. Considered in selected cases, usually where lens wear alone is not getting there.
Referred
Corneal graft (keratoplasty)
Replacing the cornea with donor tissue. Reserved for advanced disease where lenses can no longer give usable vision. It is a long way from where most people ever get to.
Referred, same day
Anything sudden
Hydrops, a painful red eye, a sudden drop in vision. Seen here promptly and referred on if it needs a hospital, rather than added to a waiting list.
On cross-linking
We don’t perform cross-linking. We refer for it, and we will organise that. In the Melbourne randomised trial, untreated eyes steepened by about 1.75 dioptres over three years and their vision slipped; cross-linked eyes flattened slightly, by about 1 dioptre, and their vision improved a little. Two eyes had minor complications and neither lost vision.
And one thing lenses cannot do. A scleral lens gives you clear, comfortable vision — often the best you have had in years. It does not stop the cone underneath from changing. In a study of 157 eyes followed for at least a year, about 15% lost some of their best lens-corrected vision as the keratoconus progressed beneath a well-fitting lens. That is exactly why we keep scanning your cornea whether or not you wear lenses.
Not sure where your keratoconus is up to?
On the booking page, choose Scleral Lens Consultation. For other keratoconus visits, call us on (02) 8765 9600.
Which contact lens is best for keratoconus?
Corneal or scleral lenses: similar sharpness, different comfort
There is no single best lens; it depends on how steep your cornea is and what you can comfortably wear all day. Rigid lenses give the clearest vision because they replace the cornea’s irregular surface with a smooth one. Between a small corneal lens and a larger scleral one, the choice is mostly about comfort and stability, not sharpness.
6/19 to 6/7.5Average vision in glasses, then in scleral lenses, across published keratoconus studies. That gain is measured against spectacles, not against other contact lenses. Results vary between individuals.
Two findings are worth knowing, because they are often misrepresented — including by people selling lenses.
Corneal rigid lenses
A small rigid lens sitting directly on the cornea. Long-established, less expensive, and optically excellent.
Sharpness: no measured disadvantage against sclerals
Comfort scored 2.2 out of 5 in a 422-person survey
If yours is comfortable and working, there is no vision reason to change
Scleral lenses
A larger lens vaulting the cone entirely, resting on the white of the eye with fluid held underneath.
Sharpness: no measured advantage over corneal rigid lenses
Comfort scored 3.3 out of 5 in the same survey
The reason to switch is comfort and wearing time, not vision
| What the research found | Corneal rigid | Scleral |
|---|---|---|
| Vision (randomised crossover trial) | No significant difference between the two | No significant difference between the two |
| Comfort (same trial) | Lower | Significantly better |
| Wearer preference | 53% | 47% |
| Comfort score, 422-person survey | 2.2 / 5 | 3.3 / 5 |
The trial behind the near-even preference recruited people already wearing corneal lenses successfully, which favours corneal lenses, as the authors said. Their conclusion: the people who benefit from switching are those whose comfort is poor. That matches what we see. If you take a lens out by mid-afternoon, or never got past the adaptation, a scleral is the next step we recommend.
In a Belgian series of 75 eyes with severe keratoconus (all corneal transplant candidates), scleral lenses were fitted to 51 eyes, and 40 of those 51 were still wearing them successfully at final follow-up, with the graft put off. Mean follow-up was about two and a half years, so the graft was put off, not avoided.
How keratoconus progression is monitored
We compare each scan with your last
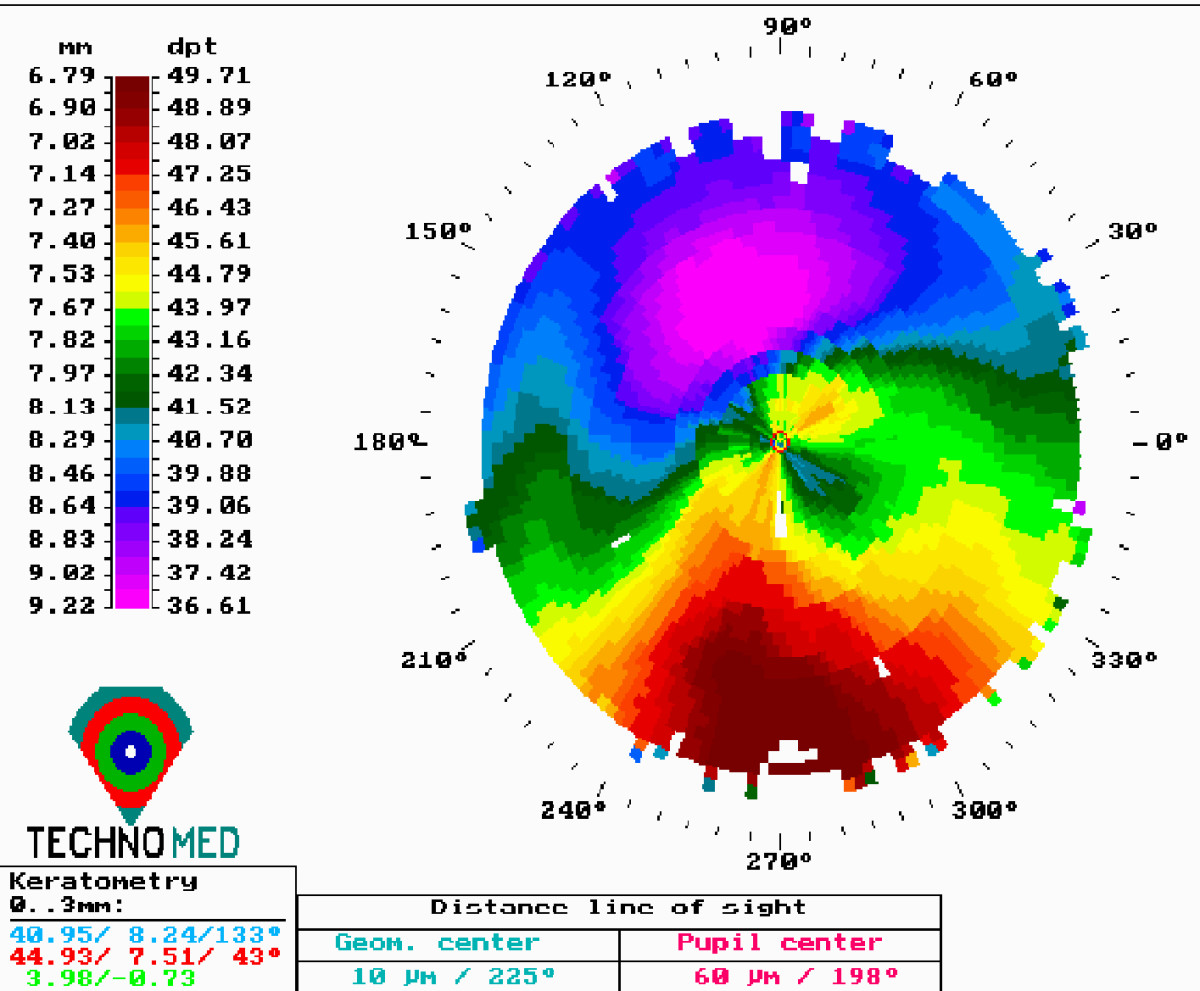
We map the shape of your cornea with a topographer and compare that map against your previous ones. Progression is a change between scans, not something anyone can judge by eye at a single visit. That is why the repeat scan is the test, and why the appointment interval matters more than any one result.
Sample · illustrative
First visit
Twelve months later
Illustration only. These are simplified drawings to show what a comparison looks like. They are not a real patient’s scans, not a diagnosis, and not a treatment result. Your own maps will look different.
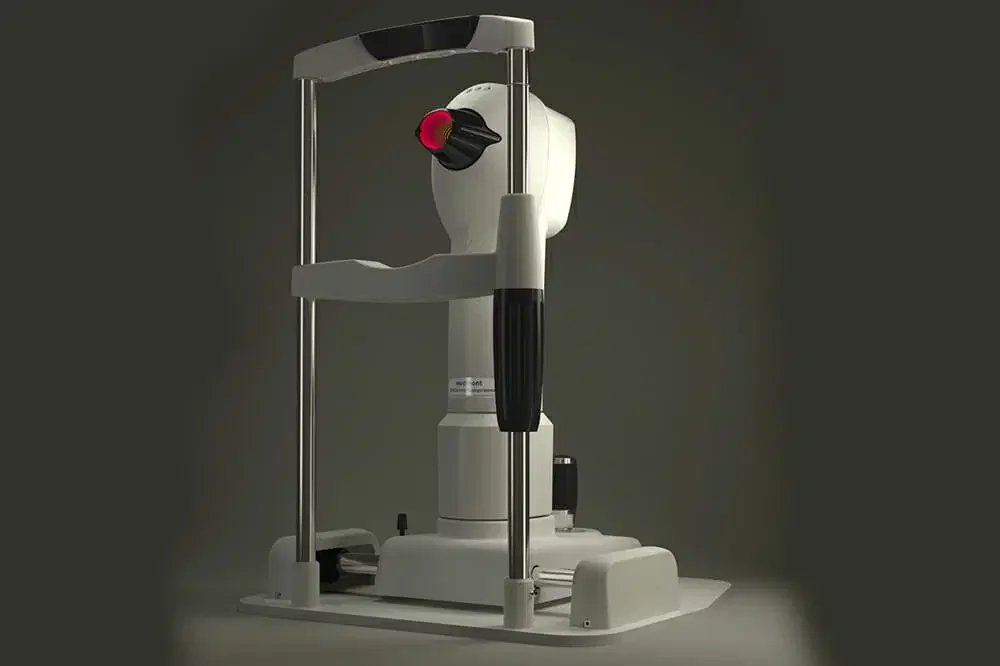
We use a Medmont corneal topographer to build a map of your cornea’s surface, and a second scan that shows the cornea in cross-section where that helps. What we are watching is whether the steepest part of the cone is getting steeper over time.
Why the comparison matters more than any single number.
One scan tells us the shape today. It cannot tell you whether that shape is stable, because keratoconic corneas vary a great deal between people. A measurement that would be alarming in one eye is another person’s baseline. The information is in the change, which is why we ask you back.
If it is progressing, we refer you for cross-linking.
That is the treatment aimed at stopping it, and organising that referral is the whole point of the monitoring. We stay involved with the surgeon afterwards, so you are not carrying messages between two practices.
If it is stable, we keep the scans going and get on with the lenses.
Stability is a finding, not a non-result. It is what lets us focus on the half that changes your day: getting you a lens that is comfortable and gives you sharp vision.
This is a measurement, not a guess. It is the reason we ask you to come back even when nothing feels different to you.
Keratoconus treatment cost
What the scleral lens program costs
If you go ahead with scleral lenses, the program is from $2,200 for both eyes. That is one price for the lenses, the fitting, six months to get the fit right, and two years of reviews. Corneal rigid lenses cost less. Cross-linking is billed by the surgeon and the hospital, not by us. Nothing is ordered, and no lens is charged for, until you have seen the numbers and said yes.
Scleral lens program · both eyes
From $2,200
Lenses, fitting, and two years of reviews included
- The assessment and all corneal scans
- Both lenses, custom made for your eyes
- Every fitting appointment, and two years of reviews
- Handling training, for as long as you need it
- Your starter solution kit
- Six months to get the fit right — changes and breakage
What happens after two years
Lenses last about two years in normal wear. When yours are due for replacement, a new two-year cycle is $1,400 covering the lenses and the reviews in that period. If your prescription changes before then, we will quote before ordering anything.
Corneal rigid lenses
Less than the scleral program, and quoted at your assessment once we know what your cornea needs.
Corneal cross-linking
Not ours to quote. Those costs sit with the surgeon and the hospital, and we will tell you who can give you the figure.
Health funds
Contact lenses for keratoconus come out of your ordinary optical extras limit. There is no separate benefit for medically necessary lenses, so for most funds that is a few hundred dollars a year. We will give you an itemised receipt.
If your eyes need something beyond the standard program, we will tell you in writing, before we order anything. That might be a cornea irregular enough to need a lens designed from a detailed surface scan, a lens fitted after a graft, or a specialised surface coating. You will never get a bill you have not already agreed to.
Keratoconus care in Sydney
What we do here, and what we refer
We look after diagnosis, corneal mapping, monitoring for progression, and fitting the lens that suits your cornea: glasses, corneal rigid or scleral.
We refer for cross-linking, ring segments and grafts, and we co-manage with your ophthalmologist so you are not carrying messages between two practices.
Here at Concord Eyecare
Diagnosis, monitoring and lenses
- The diagnosis, and an explanation you can follow
- Corneal topography, and the repeat scans that show change
- Glasses, while they are still doing the job
- Corneal rigid and scleral lens fitting, including after a graft
- The ongoing reviews that keep a lens fitting properly
Referred, and we’ll organise it
Anything surgical
- Corneal cross-linking, when your cornea is changing
- Intracorneal ring segments
- Corneal grafting
- Anything sudden: seen here promptly, referred the same day if it needs a hospital
We would rather be clear about that boundary up front than have you discover it halfway through. Plenty of keratoconus care involves two practitioners, and the handover between them is where things usually get dropped. So we hold on to that part rather than leaving it to you.

What we will tell you, either way
We assess each eye on its own and tell you clearly where things stand. That includes when the answer is that something simpler has not been tried yet, or that the lens you are already wearing is the right one and does not need changing. Keratoconus is manageable, and most of managing it well is not rushing.
Keratoconus questions answered
Common questions
Who is experienced in keratoconus in Sydney?
Keratoconus is usually managed jointly: optometrists handle the diagnosis, the monitoring and the contact lenses, while ophthalmologists perform cross-linking and surgery. At Concord Eyecare we are experienced in fitting corneal rigid and scleral lenses for irregular corneas, and we refer for the surgical side.
If you have been diagnosed and do not know where to start, an assessment with corneal mapping is the sensible first step. It tells you both where your cornea is now and whether it is changing.
What should I avoid if I have keratoconus?
Rubbing your eyes is the one thing worth changing. People with keratoconus report rubbing their eyes far more often than people without it. Across the available studies it is several times more often. What those studies cannot prove is which came first, because the trial that would settle it has never been run.
Even so, rubbing puts real mechanical force on a cornea that is already thinner than it should be, so stopping is worth doing. If your eyes itch, treat the itch rather than rubbing it. And tell us, because allergy and dry eye are both fixable.
At what age does keratoconus get worse?
It is usually most active through the teens and twenties, and tends to settle with age. In one large study the average age at diagnosis was about 28. That is when people were diagnosed, not when it started, and no reliable figure exists for when it begins.
Being young at diagnosis is the main reason we would want to monitor closely and talk about cross-linking early, while there is more still to protect.
Can keratoconus be cured?
No, and anyone telling you otherwise is overselling. But it is treatable, and that is a meaningful difference: cross-linking can stop it progressing, and lenses can restore sharp vision. Most people whose keratoconus is picked up and managed keep good vision for life. Left unwatched it is a different story, which is why the monitoring matters more than it sounds like it should.
Can I get laser eye surgery if I have keratoconus?
No. Standard laser vision correction works by removing corneal tissue, and a keratoconic cornea is already too thin. It would make things worse. Keratoconus is a specific exclusion for LASIK.
Cross-linking is the procedure that applies here instead, and it works the opposite way: it strengthens the cornea rather than thinning it.
Will glasses help my keratoconus?
Early on, yes. While glasses are doing the job there is no reason to change. As the cone steepens they stop being able to keep up, because a spectacle lens can only correct a regular shape.
When new glasses stop making a real difference, that is the point to look at rigid or scleral lenses.
How much does keratoconus treatment cost in Australia?
It depends which half you mean. Contact lens management sits with us. Our scleral lens program is from $2,200 for both eyes, covering the lenses, the fitting and two years of reviews, and corneal rigid lenses are less than that.
Cross-linking is a surgical procedure billed by the surgeon and the hospital, so those costs sit outside our practice and we will point you to who can quote them.
Further reading
More on keratoconus
Scleral lenses for irregular corneas
How the lens works, how it is fitted, what it is like to wear, and the full program fee.

Dry eye diagnosis and treatment
Many keratoconic eyes also have a dry, irritated surface. A comfortable lens needs a healthy one.
Keratoconus Australia
The independent patient support and advocacy body, not affiliated with us.
Book an assessment
Corneal mapping plus a clear answer on where your keratoconus is up to.

Reviewed by Dr Mark Joung, B.Optom (Hons) UNSW · Certificate in Ocular Therapeutics (ACO) · Therapeutically endorsed
Mark fits corneal rigid and scleral lenses for keratoconus and other irregular corneas at Concord Eyecare, and co-manages with corneal surgeons for cross-linking and surgical care.
References (7)
- Chan E, Chong EW, Lingham G, et al. Prevalence of keratoconus based on Scheimpflug imaging: the Raine Study. Ophthalmology. 2021;128(4):515–521.
- Wittig-Silva C, Chan E, Islam FMA, Wu T, Whiting M, Snibson GR. A randomised, controlled trial of corneal collagen cross-linking in progressive keratoconus. Ophthalmology. 2014;121(4):812–821.
- Fuller DG, Wang Y. Safety and efficacy of scleral lenses for keratoconus. Optometry and Vision Science. 2020;97(9):741–748.
- Levit A, Benwell M, Evans BJW. Randomised controlled trial of corneal vs scleral rigid gas permeable contact lenses for keratoconus. Contact Lens and Anterior Eye. 2020;43(6):543–552.
- Shorter E, Schornack M, Harthan J, et al. Keratoconus patient satisfaction and care burden with corneal gas permeable and scleral lenses. Optometry and Vision Science. 2020;97(9):790–796.
- Koppen C, Kreps EO, Anthonissen L, et al. Scleral lenses reduce the need for corneal transplants in severe keratoconus. American Journal of Ophthalmology. 2018;185:43–47.
- Sahebjada S, Al-Mahrouqi HH, Moshegov S, et al. Eye rubbing in the aetiology of keratoconus: a systematic review and meta-analysis. Graefe’s Archive for Clinical and Experimental Ophthalmology. 2021;259(8):2057–2067.
Not sure where your keratoconus is up to?
On the booking page, choose Scleral Lens Consultation. For other keratoconus visits, call us on (02) 8765 9600.