
THE MYOPIA CLINIC · CONCORD EYECARE
When your child's eyesight keeps getting worse
Short-sightedness that keeps increasing follows a pattern. Understanding it is the first step to changing it.
- ★ 4.9 from 200+ Google reviews
- Advanced qualifications in children's vision All of our optometrists hold advanced qualifications in children's vision
- 2,500+ children cared for by our optometrists
- 1,000+ ortho-K lenses fitted between our optometrists
WHAT IS PROGRESSIVE MYOPIA?
Not a separate condition. A pattern of change
Progressive myopia is when a child's short-sightedness increases year after year as the eye grows longer than it should. It's the same condition as myopia, getting worse faster over time. The faster it gets worse, the higher the risk of eye health complications in adulthood.
Every eye has a length: the distance from the front of the cornea to the retina at the back. In myopia, the eye is slightly too long, so light focuses in front of the retina instead of on it. That's what causes the blur.
When myopia keeps getting worse, the eye keeps growing. Each millimetre of extra length shifts the prescription further. This is why your child needs new glasses every year. The eye is physically changing shape.
Standard glasses correct the blur, but they don't address the growth. That's an important distinction. It's why understanding what myopia is matters before deciding what to do about it.
We track this growth directly with axial length measurement using the Zeiss IOLMaster 500. Prescription alone doesn't tell the full story.
HOW FAST IS TOO FAST?
What the numbers mean
Without treatment, a short-sighted child's prescription typically changes by -0.50 to -1.00 dioptres per year on average.
Prescription change is the number most parents hear at each visit. But it only tells part of the story. Axial length can increase before the prescription catches up. That's why we measure both.
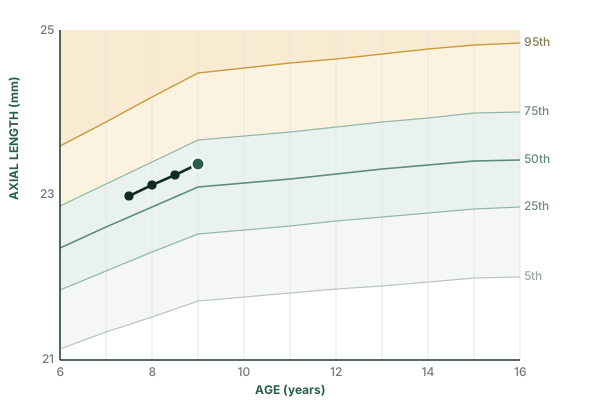
How we judge axial length progression. In children who aren't short-sighted, axial length usually increases by about 0.1 to 0.2 mm a year in primary school, slowing to about 0.1 mm a year after age 10 and stopping in the early teens (My Kids Vision; Gifford, Myopia Profile, 2023). We measure axial length every six months, plot the results on axial length charts for age and judge treatment over a full year. If your child's axial length sits right on that line, we keep watching. If axial length progression is faster than that for your child's age, or the glasses prescription changes by 0.50 D or more in a year, we talk with you and your child about adding or changing treatment. It is not automatic. First we check how the treatment is being worn and how the two eyes focus and work together. Atropine drops weaken focusing up close, so they are not right for every child (Peng, Myopia Profile, 2026). For ortho-K wearers we go by axial length only, because ortho-K reshapes the front of the eye and hides the prescription change.
We use the Zeiss IOLMaster 500 to track axial length changes precisely. It's a quick, non-contact measurement. It gives us an early warning signal that prescription alone can miss.
WHY DOES MYOPIA GET WORSE IN SOME CHILDREN?
Age, genetics, and how they use their eyes
Children who become myopic before age 9 tend to reach higher prescriptions by adulthood. Genetics play a strong role: one myopic parent roughly triples the risk, two parents increase it six-fold. But environment matters too: less outdoor time and more sustained near work make it get worse faster, especially during growth spurts.
Age of onset is the strongest predictor. A child who becomes myopic at six has many more years of axial length progression ahead than one who starts at twelve. More years of growth means a higher final prescription and a higher risk of complications. This is why early detection matters so much.
Genetics set the baseline. If one parent is myopic, their child's risk roughly triples. If both parents are, the risk increases six-fold (Mutti et al., 2002). Ethnicity also plays a role. The Sydney Myopia Study found that 42.7% of East Asian children were myopic by age 12, compared to 4.4% of European children (Rose et al., 2008).
Environment accelerates the timeline. Less than two hours of outdoor time per day significantly increases myopia risk. Sustained near work (screens, reading, devices held close) adds to the load. These factors don't cause myopia on their own, but they can turn a slow change into a fast one.
Growth spurts matter. How fast myopia gets worse isn't always predictable from year to year.
"Myopia doesn't always get worse in a straight line. We see children whose prescription barely changes for a year or two, then jumps significantly, often catching up to the average rate. Growth spurts and changes in visual habits both play a role, which is why we monitor every six months rather than once a year."
WHY NEW GLASSES DON'T SLOW IT DOWN
The glasses fix the blur, not the growth
Standard single-vision glasses and contact lenses correct blurry vision, but they do nothing to slow the eye's elongation. A child who gets new glasses every year is seeing clearly today, but accumulating risk for tomorrow. Myopia control treatments are a different class. They are designed to slow the eye's physical growth.
This is the part that surprises most parents. Glasses do their job. Your child sees the board, reads comfortably, plays sport without squinting. But the prescription keeps changing because nothing is addressing why it's changing.
Myopia control is a different kind of treatment. It's specifically designed to slow the elongation of the eye. The treatments use optical, pharmaceutical, or combination approaches backed by clinical research.
"The prescription numbers don't mean much to most parents. That's completely normal. But when I project where their child's myopia is heading, and explain that above about -6.00 dioptres they may not be eligible for laser eye surgery as an adult (depending on their corneal thickness), that's when it clicks. It's about keeping their options open later, as well as the glasses they need now."
Ortho-K
Night-wear lenses that reshape the cornea while sleeping. Clear vision all day without glasses. Research suggests slower axial length progression.
MiyoSmart Lenses
Spectacle lenses with HOYA's DIMS technology. Worn like normal glasses. HOYA data suggests slower axial length progression with 12+ hours daily wear.
MiSight Contact Lenses
Daily disposable soft lenses by CooperVision. In a three-year trial, eyes grew more slowly than in single-vision contact lenses (Chamberlain et al., 2019).
Atropine Eye Drops
Low-dose drops used once daily at bedtime. Works alone, or combined with other treatments when the eyes are getting worse quickly. In the LAMP study, eyes grew more slowly than with placebo drops.
WHEN DOES MYOPIA STOP GETTING WORSE?
Usually mid-teens. Not always
Myopia typically stops getting worse between ages 16 and 17. However, some patients keep getting more short-sighted well into their twenties. Children who become myopic earlier tend to keep getting worse for longer and reach higher final prescriptions, which is why early intervention matters most, ideally before age 9.
There's no exact age when myopia stops getting worse for everyone. Most children see their prescription level out in the mid-to-late teenage years, as the eye finishes most of its growth. But we regularly see patients whose myopia continues to shift into their early twenties.
This is why "waiting to see if it settles" can be a costly strategy. By the time it slows naturally, the prescription may already be high enough to carry long-term risk. Myopia control treatments work best while the eye is still growing. That window is finite.
Under age 6: Significant myopia in very young children is unusual and warrants a thorough ocular health examination to rule out pathological causes. In some cases, we recommend a second opinion with a paediatric ophthalmologist before starting any myopia control treatment.
For children already in treatment, we continue monitoring at regular intervals and adjust the approach as the rate of change shifts. Atropine eye drops can be added to spectacle or contact lens treatments when the eyes are getting worse fast enough to warrant combination therapy.
WHAT IS HIGH MYOPIA AND WHY DOES IT MATTER?
Above -6.00 dioptres, the risks change
High myopia (generally above -6.00 dioptres) materially increases the lifetime risk of retinal detachment, myopic maculopathy, glaucoma, and early cataracts. It also typically puts LASIK and other laser eye surgery options out of reach, depending on corneal thickness. The goal of myopia control is to keep the final prescription as low as possible.
For many parents, the most concrete way to understand -6.00 is this: it's roughly the threshold above which laser eye surgery becomes unlikely. LASIK eligibility depends on both the prescription and how thick the cornea is. At higher prescriptions, there often isn't enough corneal tissue to safely reshape. So a child whose myopia tracks past -6.00 may be looking at a lifetime of glasses or contact lenses with no surgical option.
Beyond the practical issue of correction, high myopia carries real health risks. The longer the eye grows, the more the retina stretches and thins. This makes it more vulnerable to:
Retinal detachment: the retina separates from the back of the eye. A medical emergency that requires surgery.
Myopic maculopathy: progressive damage to the central retina that can cause irreversible vision loss.
Glaucoma: myopic eyes are more susceptible to this silent optic nerve disease.
Early cataracts: clouding of the natural lens tends to develop earlier and more aggressively in highly myopic eyes.
These risks are why myopia control aims to reduce the lifetime probability of something going wrong, as well as the strength of the glasses.
HOW CONCORD EYECARE MONITORS YOUR CHILD'S EYES
Baseline, monitoring, and acting at the right time
At the Concord Myopia Clinic, we establish a baseline with axial length measurement using the Zeiss IOLMaster 500, then monitor every six months. If axial length progression is faster than normal for age (about 0.1 to 0.2 mm a year in primary school, about 0.1 mm after 10), we talk with you about adding or changing treatment, after checking how your child's eyes focus together.
1
Baseline assessment
Full refraction, axial length measurement with the Zeiss IOLMaster 500, and corneal topography. This gives us an objective starting point: a prescription plus a map of the eye's shape and length.
2
Six-monthly monitoring
We review every six months rather than annually. Myopia doesn't always get worse at a steady rate, and catching a jump early means we can adjust the treatment plan before significant change accumulates.
All three of our optometrists are therapeutically endorsed, which means we can prescribe atropine directly.

Dr Nikki Peng
B.Optom (Hons 1st Class) UNSW · Grad Cert Ocular Therapeutics · ACO Advanced Children's Vision

Dr Vivian Li
B.Optom (Hons) UNSW · Therapeutically endorsed · ACO Advanced Children's Vision Certificate

Dr Mark Joung
B.Optom (Hons) UNSW · Certificate in Ocular Therapeutics (ACO)
FREQUENTLY ASKED QUESTIONS
What parents ask about progressive myopia
QWhat is progressive myopia?
It's a pattern where a child's short-sightedness gets worse year after year, driven by the eye growing too long. It's myopia that is getting worse faster over time, not a separate disease. The faster it gets worse, the higher the lifetime risk of complications like retinal detachment and myopic maculopathy. Learn more about what myopia is and how it works.
QAt what age does myopia stop getting worse?
Myopia typically stops getting worse between ages 16 and 17, but some patients keep getting more short-sighted well into their twenties. Children who become myopic earlier tend to keep getting worse for longer and reach higher final prescriptions, which is why starting myopia control early makes a real difference.
QCan myopia progression be stopped?
Current treatments can't stop myopia getting worse entirely, but they can significantly slow it. Ortho-K, MiyoSmart, MiSight and atropine eye drops are each clinically shown to slow it. The goal is to keep the final prescription as low as possible.
QWhat causes myopia to get worse quickly?
The main risk factors are early age of onset, family history (especially two myopic parents), limited outdoor time, and sustained near work. Ethnicity also plays a role. The Sydney Myopia Study found higher prevalence in East Asian children. Growth spurts can cause prescription jumps even when the prescription seemed stable.
QShould I be worried about my child's myopia?
Any increase is worth monitoring, especially in children under 10. If your child's prescription is increasing by 0.50 dioptres or more per year, the eyes are getting worse fast and active treatment is recommended. A myopia assessment with axial length measurement gives you a clear picture of where things stand.
QWhat is high myopia and why does it matter?
High myopia (generally above -6.00 dioptres) significantly increases the lifetime risk of retinal detachment, myopic maculopathy, glaucoma, and early cataracts. It also typically rules out laser eye surgery like LASIK, depending on corneal thickness. The aim of myopia control is to keep the final prescription below this threshold.


Dr Nikki Peng, B.Optom (Hons 1st Class) UNSW · Grad Cert Ocular Therapeutics · ACO Advanced Children's Vision
Nikki leads myopia management at Concord Eyecare with a focus on evidence-based treatment plans for children and young adults.
Reviewed by Dr Nikki Peng & Dr Vivian Li · Last updated May 2026
The 2,500+ and 1,000+ figures come from our optometrists' practice records across their careers (October 2026).
References (8)
- Brennan NA, Toubouti YM, Cheng X, Bullimore MA. (2021). Efficacy in myopia control. Progress in Retinal and Eye Research, 83, 100923.
- Mutti DO, Mitchell GL, Moeschberger ML, Jones LA, Zadnik K. (2002). Parental myopia, near work, school achievement, and children's refractive error. Investigative Ophthalmology & Visual Science, 43(12), 3633–3640.
- Rose KA, Morgan IG, Ip J, et al. (2008). Outdoor activity reduces the prevalence of myopia in children. Ophthalmology, 115(8), 1279–1285.
- Lam CSY, Tang WC, Tse DY, et al. (2020). Defocus Incorporated Multiple Segments (DIMS) spectacle lenses slow myopia progression: a 2-year randomised clinical trial. British Journal of Ophthalmology, 104(3), 363–368.
- Chamberlain P, Peixoto-de-Matos SC, Logan NS, et al. (2019). A 3-year randomized clinical trial of MiSight lenses for myopia control. Optometry and Vision Science, 96(8), 556–567.
- Yam JC, Jiang Y, Tang SM, et al. (2019). Low-Concentration Atropine for Myopia Progression (LAMP) Study: A Randomized, Double-Blinded, Placebo-Controlled Trial of 0.05%, 0.025%, and 0.01% Atropine Eye Drops in Myopia Control. Ophthalmology, 126(1), 113–124.
- Flitcroft DI. (2012). The complex interactions of retinal, optical and environmental factors in myopia aetiology. Progress in Retinal and Eye Research, 31(6), 622–660.
- Sankaridurg P, Tahhan N, Engardahl S, et al. (2021). IMI — Update on myopia prevention. Investigative Ophthalmology & Visual Science, 62(5).
Serving Sydney families from our North Strathfield practice at 161 Concord Rd, North Strathfield NSW 2137. Free parking nearby. 6 minutes from North Strathfield Station.
Your child's eyesight doesn't have to be a guessing game
A myopia assessment with axial length measurement gives you a clear picture and a plan.