
Myopia control · act early
When to start myopia control
We can often see short-sightedness coming before it starts, so we can act early instead of waiting for glasses.
- ★ 4.9 from 200+ Google reviews
- Advanced qualifications in children's vision All of our optometrists hold advanced qualifications in children's vision
- 2,500+ children cared for by our optometrists
- 1,000+ ortho-K lenses fitted between our optometrists
Pre-myopia
What is pre-myopia?
Your child still sees clearly, but their eyes show signs of heading towards short-sightedness (Flitcroft et al. 2019).
Clear sight
A healthy buffer of long-sightedness for their age.
Pre-myopia
Still clear sight, with a small buffer for their age and other risk factors.
Myopia
The buffer is used up and distance vision blurs.
Most children are born a little long-sighted. This hyperopic reserve is used up as the eye grows. How much is enough depends on age, so we read it against your child's age, not one fixed number (Tahhan et al., 2025).
Early signs
How can you tell before it starts?
Two measurements: the buffer first, and eye length to show how the eye is growing.
The buffer, measured with eye drops
For a child's age, it is the best early sign of who is likely to become short-sighted (Zadnik et al., 2015).
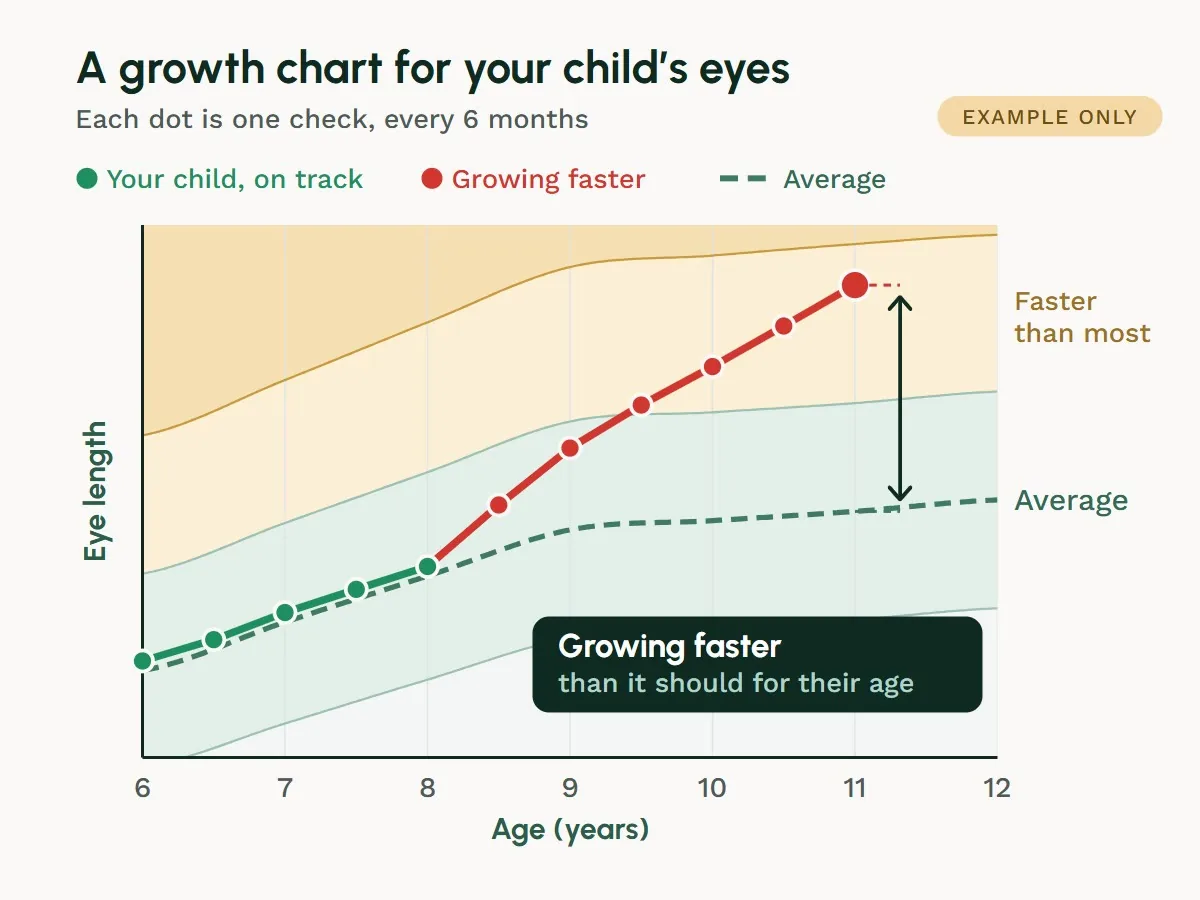
Eye length, on a growth chart
Our ZEISS IOLMaster 500 measures it. Plotted over time, it shows whether the eye is growing faster than most (McCullough et al., 2020).
No single measurement is certain. Together they build the picture, and this pairing is what our SightTrack assessment does.
Axial length
What happens to the eye before the prescription changes?
Eyes that become short-sighted tend to grow faster in the years before the prescription changes (Mutti et al., 2007).
Dutch children, measured at 6 and again at 9
0.34 mm a year
Eyes that became short-sighted grew almost twice as fast.
Children who stayed clear-sighted grew 0.19 mm a year.
Tideman et al. 2018, Acta Ophthalmologica
That is why a growth chart can show a change before a vision test does.
Why timing matters
Why does the age myopia starts matter?
The younger it starts, the more myopia tends to build up by adulthood.
7 to 10
Fastest years
Short-sightedness tends to get worse fastest at ages 7 to 10 (Brennan et al., 2021).
1.31 D
More myopia from age alone
In the COMET trial, 6 and 7-year-olds gained 1.31 D more myopia over three years than 11-year-olds (Hyman et al., 2005).
Singapore children, followed to age 11
2.9×
Each year earlier myopia started, the odds of high myopia by age 11 were about 2.9 times higher.
A finding across groups of children, not a forecast for one child.
Chua et al. 2016, Ophthalmic Physiol Opt
In studies that followed children over time, myopia that started later tended to end lower in adulthood (Bullimore and Brennan, 2023). This is an association, not proof that delaying the start lowers adult myopia, and the effect is smaller in some populations.
Each dioptre avoided is linked to a lower lifetime risk of myopic maculopathy (Bullimore and Brennan, 2019).
Acting early
What can be done before myopia starts?
Daily habits and regular checks. The assessment decides whether anything more makes sense.
Time outdoors
In a large school trial, extra time outdoors lowered the number of children who became short-sighted (He et al., 2015).
Sleep
Later bedtimes are linked with more short-sightedness in Chinese school children (Li et al., 2022). A link, not proof, and regular sleep suits growing children anyway.
Checks every six months
For a child at risk, we measure the buffer and eye length every six months, or yearly if the risk is very low.
We also talk through screen time and close work. We don't prescribe eye drops to slow myopia for children who are not yet short-sighted.
What to expect
Will acting early stop my child becoming short-sighted?
Not necessarily, and we don't promise it.
Researchers don't yet know whether delaying the start lowers myopia in adulthood. Some children with a small buffer never become short-sighted (Tahhan et al., 2025). We watch closely and treat the children who need it.
By age
Which myopia treatment works best at which age?
Age sets the starting point. Maturity, prescription and how fast the eyes are changing decide the rest.
From age 4
Myopia control glasses
MiyoSmart (HOYA) or Stellest (Essilor). They work only when worn, so wear time matters.
From age 6
Ortho-K or MiSight daily contacts
Ortho-K works overnight with no daytime lens management. MiSight 1 day is a daily disposable. Both require the child to cope with lenses.
Higher prescriptions
Contact lenses
Higher prescriptions make spectacle lenses thick and heavy. Ortho-K or MiSight often suit better.
Eyes changing quickly
Combination treatment
If one treatment slows growth too little, low-dose atropine can be added, prescribed when suitable (LAMP study, Yam et al., 2019).
Teenagers
Any option above
Growth slows in the teens, but half of children are still changing at 15 (COMET Group, 2013). Still worth starting.
In our practice
Most of our myopia control patients are 7 to 12. We treat up to age 20 and have fitted ortho-K from age six. Under 5, we first rule out other causes with a full cycloplegic examination and may refer to a paediatric ophthalmologist.

The arithmetic
Why start in the fast years instead of waiting?
Treatment slows a share of the change, so it saves the most when eyes change fastest.
Fastest at 7 to 10
These years hold the most axial length progression to slow (Brennan et al., 2021).
Treatment slows a share
Each option slows axial length progression. None stops it completely.
More change, more saved
The same treatment in the fast years avoids more myopia overall.
This is arithmetic from group averages, not a forecast for one child. The researchers' own words are that each dioptre matters (Bullimore and Brennan, 2019).
Is it time? An assessment tells you.
First visit
What happens at a myopia assessment?
About an hour. You leave knowing where your child stands and what we would do.
30 seconds an eye
Eye length
Our ZEISS IOLMaster 500 measures eye length to track growth.
With eye drops
True prescription
Drops relax focusing muscles that can hide a child's true prescription.
Talking with you
Risk factors
Family history, outdoor time, near work and age of onset.
Before you leave
Your child's plan
Agree suitable options and what to expect.
No obligation that day; many families decide at home a week or two later.
Common questions
Common questions about starting myopia control
At what age does myopia start?
Usually in primary school. In Singapore's SCORM study, myopia began at an eye length of about 24.0 mm in boys and 23.7 mm in girls, regardless of age (Saw et al., 2005).
At what age does myopia get worse fastest?
At ages 7 to 10 (Brennan et al., 2021). In the COMET trial, the eyes of 6 and 7-year-olds became 1.31 D more short-sighted over three years than those of 11-year-olds (Hyman et al., 2005).
At what age does myopia stop progressing?
Later than most parents expect. In COMET, half had stopped changing by 15, three-quarters by 18 and 90% by 21 (COMET Group, 2013). In a Perth study, more than a third of young adults had their eyes shift towards short-sightedness between 20 and 28, mostly by a small amount (Lee et al., 2022). From 18, stopping becomes an option; if eye length is still growing, further myopia control may be needed.
Should I wait to see if it gets worse first?
No. Waiting leaves the fastest years untreated. Myopia control is worthwhile without a minimum prescription.
Is it too late to start at 14?
No. Half of children are still changing at 15 and a quarter at 18 (COMET Group, 2013). A 14-year-old whose eyes are still getting worse has myopia to avoid.
Can a 6-year-old wear ortho-K lenses?
Yes. We have fitted ortho-K from age six with parental help.
What are the best myopia control lenses for kids?
No lens is best for everyone. The choice depends on age, prescription and daily wear. See myopia control glasses compared.
Is there an average myopia prescription to worry about?
No average is safe. We act from −0.50 D. COMET children treated only with ordinary or progressive glasses settled at an average −4.87 D (COMET Group, 2013).
Does myopia control cure myopia?
No. Myopia control slows axial length progression without reversing existing myopia.
What if my child is not short-sighted yet?
We measure their hyperopic reserve and eye length, and grade the risk. A child at risk is checked every six months, or yearly if the risk is very low.
My child sees clearly. Why check?
A child can see clearly and still have a small buffer for their age, so a normal school vision check does not rule out pre-myopia.
How long does myopia control treatment last?
Usually through the school years. Once your child is 18 or older, stopping becomes an option. If eye length is still growing, the eyes are still getting worse and further myopia control may be needed, so some continue into their early twenties.
What if one treatment isn't working?
We measure eye length at every review. If growth is still too fast, we step up treatment: we add low-dose atropine when suitable, or switch to a different option.




Reviewed by Dr Mark Joung, B.Optom (Hons) UNSW · Certificate in Ocular Therapeutics (ACO) · Advanced Paediatric Eye Care · Updated November 2026
Mark is the principal optometrist at Concord Eyecare and one of the first optometrists in Australia to fit MiyoSmart, both the original and MiyoSmart iQ.
The 2,500+ and 1,000+ figures come from our optometrists' practice records across their careers (October 2026).
References (17)
- Brennan NA, Toubouti YM, Cheng X, Bullimore MA. Efficacy in myopia control. Prog Retin Eye Res. 2021;83:100923.
- Bullimore MA, Brennan NA. Myopia control: why each dioptre matters. Optom Vis Sci. 2019;96(6):463–465.
- Bullimore MA, Brennan NA. Myopia: an ounce of prevention is worth a pound of cure. Ophthalmic Physiol Opt. 2023;43(1):116–121. doi:10.1111/opo.13058 (abstract)
- Chua SYL, Sabanayagam C, Cheung YB, et al. Age of onset of myopia predicts risk of high myopia in later childhood in myopic Singapore children. Ophthalmic Physiol Opt. 2016;36(4):388–394. doi:10.1111/opo.12305
- COMET Group. Myopia stabilization and associated factors among participants in the Correction of Myopia Evaluation Trial (COMET). Invest Ophthalmol Vis Sci. 2013;54(13):7871–7884.
- Flitcroft DI, He M, Jonas JB, et al. IMI – Defining and classifying myopia. Invest Ophthalmol Vis Sci. 2019;60(3):M20–M30.
- He M, Xiang F, Zeng Y, et al. Effect of time spent outdoors at school on the development of myopia among children in China: a randomized clinical trial. JAMA. 2015;314(11):1142–1148.
- Hyman L, Gwiazda J, Hussein M, et al. Relationship of age, sex, and ethnicity with myopia progression and axial elongation in the Correction of Myopia Evaluation Trial. Arch Ophthalmol. 2005;123(7):977–987.
- Lee SS, Lingham G, Sanfilippo PG, et al. Incidence and progression of myopia in early adulthood. JAMA Ophthalmol. 2022;140(2):162–169.
- Li R, Chen Y, Zhao A, et al. Relationships between sleep duration, timing, consistency, and chronotype with myopia among school-aged children. J Ophthalmol. 2022;2022:7071801.
- McCullough S, Adamson G, Breslin KMM, et al. Axial growth and refractive change in white European children and young adults: predictive factors for myopia. Sci Rep. 2020;10:15189.
- Mutti DO, Hayes JR, Mitchell GL, et al. Refractive error, axial length, and relative peripheral refractive error before and after the onset of myopia. Invest Ophthalmol Vis Sci. 2007;48(6):2510–2519.
- Saw SM, Tong L, Chua WH, et al. Incidence and progression of myopia in Singaporean school children. Invest Ophthalmol Vis Sci. 2005;46(1):51–57.
- Tahhan N, Bullimore MA, He X, et al. IMI-2025 Digest. Invest Ophthalmol Vis Sci. 2025;66(12):27.
- Tideman JWL, Polling JR, Vingerling JR, et al. Axial length growth and the risk of developing myopia in European children. Acta Ophthalmol. 2018;96(3):301–309.
- Yam JC, Jiang Y, Tang SM, et al. Low-Concentration Atropine for Myopia Progression (LAMP) study. Ophthalmology. 2019;126(1):113–124.
- Zadnik K, Sinnott LT, Cotter SA, et al. Prediction of juvenile-onset myopia. JAMA Ophthalmol. 2015;133(6):683–689.
Serving Sydney families: Concord · Drummoyne · Abbotsford · Burwood · Five Dock · Strathfield · Homebush · Rhodes
Ready to find out if it is time?
A one-hour Myopia Assessment includes eye length measurement.