
Children's myopia control · Sydney
Which myopia treatment is right for your child?
Ortho-K, MiyoSmart and MiSight all slow short-sightedness by a similar amount. The right one comes down to your child: their age, their prescription, and what fits your family's routine.

- ★ 4.9 from 200+ Google reviews
- Advanced qualifications in children's vision All of our optometrists hold advanced qualifications in children's vision
- 2,500+ children cared for by our optometrists
- 1,000+ ortho-K lenses fitted between our optometrists
The short answer
Four things that guide treatment
Age
Glasses from about 4. Contacts from about 6.
Prescription
Options suit different prescription ranges.
Routine
Fits your family's day and night.
Consistency
What your child will use matters most.
Research shows broadly similar slowing with all three. Each works only when used. Your optometrist must decide which is appropriate for your child.
Three treatments for short-sightedness
Myopia treatments compared
How each one is worn, from what age and for which prescriptions. Costs are set out further down.
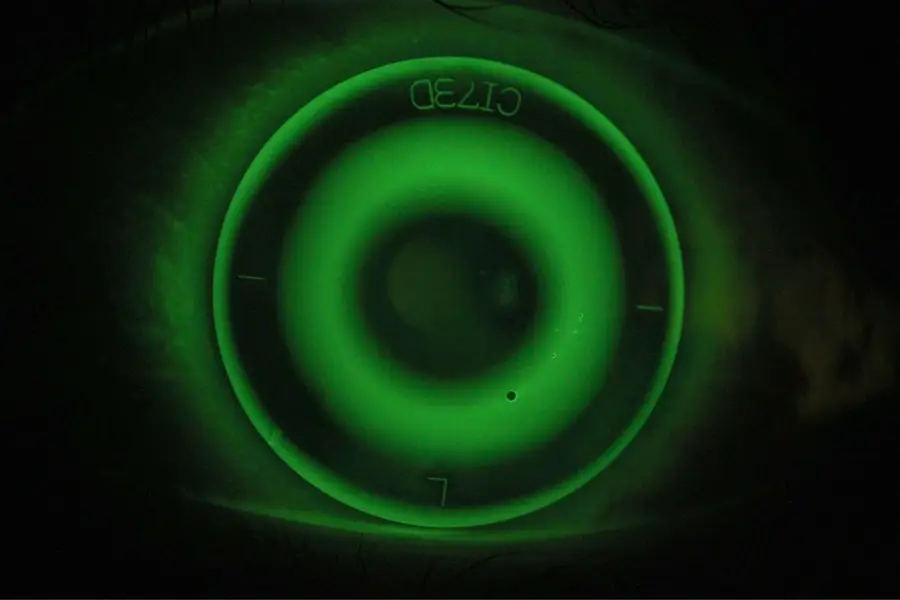
Ortho-K
Overnight contacts. No daytime lens care.
- Worn
- Overnight only. Parents help insert and remove them at home.
- From age
- About 6, depending on the child
- Prescription
- About −1.00 to −6.00; higher with custom lenses

MiyoSmart iQ
All-day treatment glasses.
- Worn
- All waking hours; works best 12+ hours a day
- From age
- About 4. Glasses only.
- Prescription
- A wide range
MiSight
Daily disposable contacts.
- Worn
- Daytime; managed by your child
- From age
- About 6, depending on the child
- Prescription
- Lower to moderate
Lens photo: HOYA.
Full comparison
| Ortho-K | MiyoSmart iQ | MiSight | |
|---|---|---|---|
| How it works | Overnight contacts gently reshape the eye's clear front surface during sleep. Temporary and reversible. | Glasses with hundreds of tiny treatment zones signalling slower eye growth. | Soft daily contacts with a built-in treatment zone. |
| When worn | Overnight only | All waking hours (12+ hours a day) | Daytime; insert and remove like ordinary contacts |
| Who handles it | Parents help insert and remove lenses at home, morning and night. No school-time lens care. | Wear the glasses. | Your child manages daytime lens care. |
| Best suited to | Families preferring parent-supervised care at home | Children happy in glasses or unsuited to contacts | Independent, active children wanting a daily lens routine |
| From age | About 6, depending on the child | About 4 | About 6, depending on the child |
| Prescription | −1.00 to −6.00; higher with custom lenses | Wide range | Lower to moderate |
Treatment choice
Which treatment suits your family?
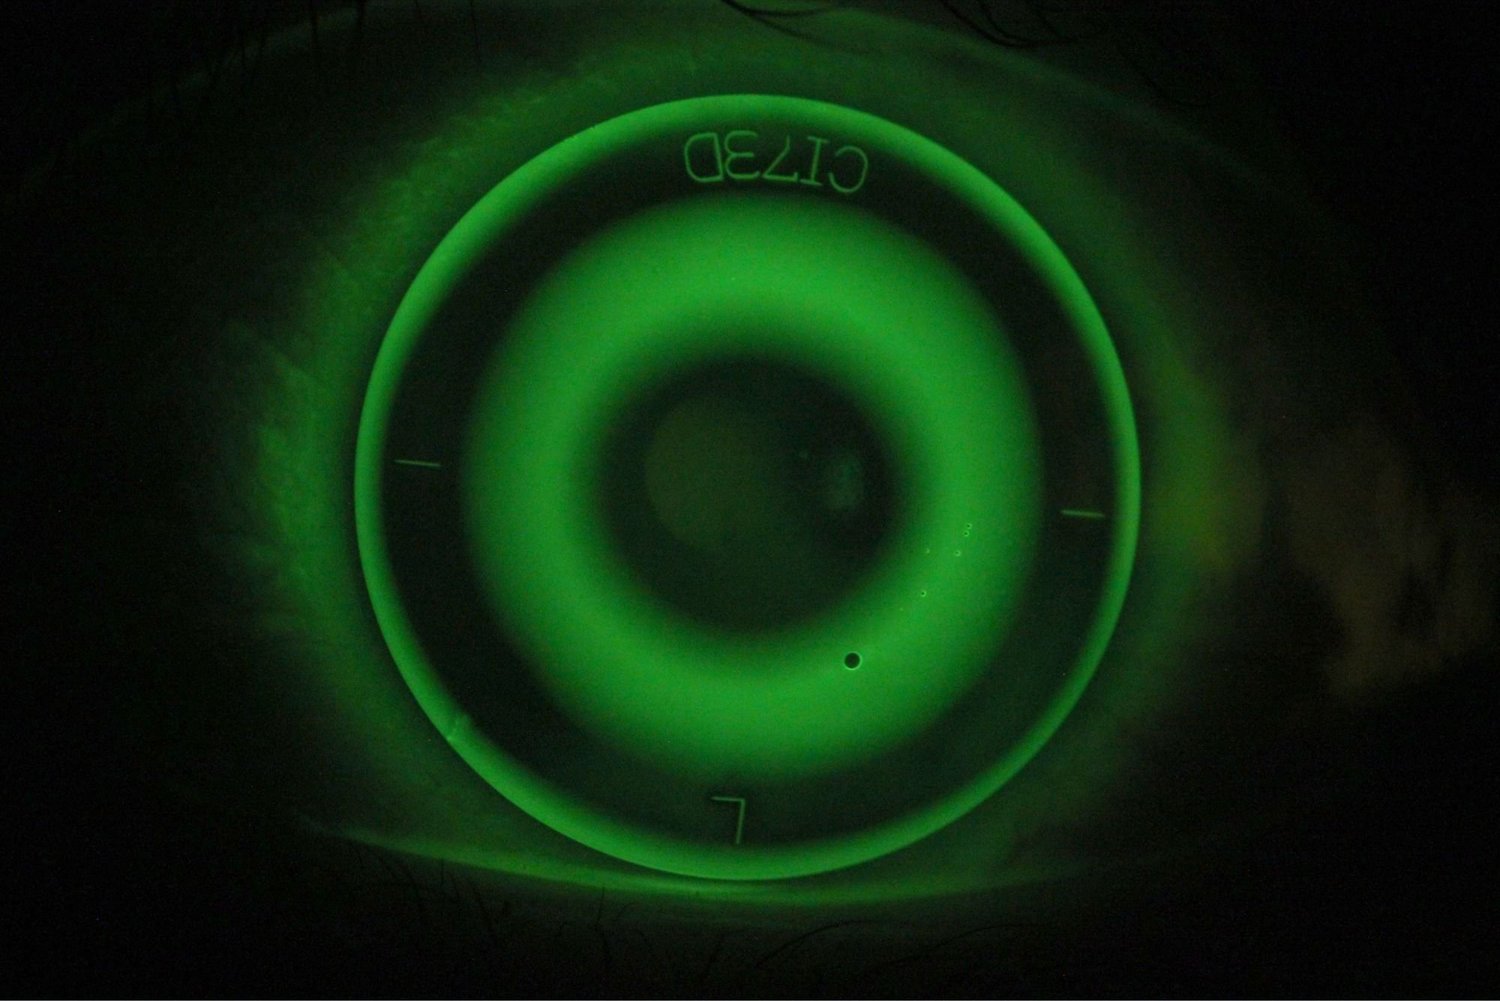
Ortho-K
Parent-supervised care at home.
- No lenses to wear or manage at school
- Parents help insert and remove lenses at home
- Needs a steady 7 to 8 hours' sleep

MiyoSmart iQ
For children happy to wear glasses.
- Contacts unsuitable or unwanted
- Careful with their glasses
- From about 4

MiSight
For active children managing daily contacts.
- Happy wearing daytime contacts
- Sport, with no glasses to fog or break
- Can handle contacts, from about 6
How we decide
How we decide which treatment suits your child
Every option here slows myopia in clinical trials. Daily life decides which suits your child.
Age
Is your child 6 or older?
If the answer is No
MiyoSmart iQ, Stellest 2.0, ZEISS MyoActive
Worn every waking hour. The frame has to fit well and stay put.
If the answer is Yes
Contact lenses
Is your child open to contact lenses?
If the answer is No
MiyoSmart iQ, Stellest 2.0, ZEISS MyoActive
Worn every waking hour. The frame has to fit well and stay put.
If the answer is Yes
Worn overnight, out in the morning
Parents run it at home, about five minutes night and morning. Nothing to wear during the day.
A fresh lens each morning
Worn through the school day. Your child takes it out on their own if it bothers them.
Whichever you choose:
If your child's eyes keep getting worse despite consistent wear, your optometrist may add atropine drops or move your child to another option.
Not sure which fits your child?
What each option costs
What each option costs, year by year
Glasses are bought per pair, so a new prescription after the first year means a new pair.
Ortho-K
$800 to $1,100
a year, first two years
From year 3, $500 to $750 a year
Two-year packages of $1,600, $1,900 or $2,200, depending on how complex the fitting is, with lens design, lenses and scheduled reviews. From year 3, $1,000 to $1,500 per two years.
MiyoSmart iQ
$750 + frames ($150–$210)
per pair
A new pair at full price if the prescription changes after 12 months
Includes the Spark coating with a 12-month scratch warranty, and a free remake if the prescription changes by 0.50 D or more within 12 months.
MiSight
$1,140
a year
Plus a one-off $150 fitting fee
$285 a quarter for lenses and care. Stop any time.
Axial length scans are $45 each, every six months ($90 a year; optional with MiyoSmart). Health fund extras rebates apply.
Checking progress
Measuring treatment progress
We measure axial length at every review to check progress before the next prescription change.
$45per scan, every six months
What about eye drops?
Where atropine fits in
- Not usually a stand-alone first choice. Low-dose atropine is a legitimate option, but we most often add it alongside glasses or lenses.
- When a child's eyes keep getting worse despite treatment, drops can be added. They are prescribed and discussed during a consultation.
- About $50 a month.
Important: atropine drops slow eye growth but don't correct vision. Your child will still need glasses or contacts for clear sight, so factor that cost in too.
What the research shows
What the research shows: all roughly equivalent.
Consistency is key.
Each slowed eye growth by a broadly similar amount in its own trial. No study has compared them directly. Results depend on daily use, so we favour what your child will use reliably.
Combining treatments when eyes worsen quickly
If short-sightedness keeps worsening, we sometimes add low-dose atropine to ortho-K. A randomised study found more slowing than ortho-K alone, clearest in younger children with lower prescriptions (Kinoshita et al., 2020). Axial length checks help us spot when combined treatment might help.
The three trials
Ortho-K: in a two-year trial of children with astigmatism, eyes grew more slowly than in single-vision glasses (Chen et al., 2013).
MiyoSmart: in a two-year trial, eyes grew more slowly than in single-vision glasses (Lam et al., 2020).
MiSight: in a three-year trial, eyes grew more slowly than in single-vision contact lenses (Chamberlain et al., 2019).
This is published research, not our own patient outcomes. Results vary because every child is different.
Questions parents ask most
The things worth asking
Which option is most effective?
They're close. Research puts all three in a similar range with no head-to-head study. The most effective treatment is usually the one your child uses consistently.
At what age can my child start?
MiyoSmart suits children from about age 4. Ortho-K (with parent-assisted handling) and MiSight both start from about age 6, depending on the child.
Can treatments be combined?
Yes. When a child's eyes keep getting worse, we sometimes add low-dose atropine alongside glasses or lenses. It's been shown to slow eye growth more than Ortho-K alone in younger, lower-prescription children.
How do you know if it's working?
We measure your child's eye growth (axial length) at every review, tracking the actual change rather than waiting for the next prescription jump.
Is Ortho-K safe for children?
Yes, when fitted and monitored properly and worn as directed. We'll talk you through care and what to watch for at the fitting. The main risk is infection, including rare infections that can threaten vision. Careful hygiene and regular reviews help reduce the risk. Read the ortho-K safety guide
Do atropine drops replace glasses?
No. Atropine slows eye growth but doesn't correct vision, so your child still needs glasses or contacts for clear sight. That's why it's usually an add-on, not a stand-alone.
Further reading
Where to read next.
Ortho-K for children & adults
Overnight lenses that gently reshape the eye while your child sleeps. How they work, safety and cost.

MiyoSmart iQ glasses
Our default myopia-control lens: the technology, who it suits, and what it costs.

MiSight daily contact lenses
Soft daily lenses with a built-in treatment zone: fitting, care and what to expect.
Compare the glasses brands
Leaning towards glasses? Compare MiyoSmart, Stellest and MyoCare side by side.

Reviewed by Dr Mark Joung · Last updated July 2026
The 2,500+ and 1,000+ figures come from our optometrists' practice records across their careers (October 2026).
- Chen C, Cheung SW, Cho P. Myopia control using toric orthokeratology (TO-SEE study). Invest Ophthalmol Vis Sci. 2013;54(10):6510-6517.
- Lam CSY, Tang WC, Tse DY, et al. Defocus Incorporated Multiple Segments (DIMS) spectacle lenses slow myopia progression: a 2-year randomised clinical trial. Br J Ophthalmol. 2020;104(3):363-368.
- Chamberlain P, Peixoto-de-Matos SC, Logan NS, et al. A 3-year randomized clinical trial of MiSight lenses for myopia control. Optom Vis Sci. 2019;96(8):556-567.
- Kinoshita N, Konno Y, Hamada N, et al. Sci Rep. 2020;10:12750 (ortho-K with 0.01% atropine, two-year randomised trial).
Not sure which is right for your child? Let's work it out together.
Families travel from across Sydney for children's myopia control at Concord Eyecare in North Strathfield.